creation date: 2026-02-02 17:58
tags: Pharmacology
Analgesics
Background
Analgesics are medications used in pain management. This page specifically discusses pharmacological options.
WHO Analgesic Ladder
The WHO is a ladder which recommends categories of analgesic based on the severity of symptoms. Inadequate pain control warrants escalation up a step.
| Step | Severity | Non-opioids | Mild opioids | Strong opioids |
|---|---|---|---|---|
| 1 | Mild | Include | Avoid | Avoid |
| 2 | Moderate | Include | Consider | Avoid |
| 3 | Severe | Include | Consider | Consider |
| If required, adjuvant drugs can be added to the choice of analgesic above. |
Non-Opioid
Acetaminophen
Mechanism of Action
- Inhibits peroxidase activity of cyclooxygenase enzyme (especially COX-2) which reduce prostaglandin synthesis (prostaglandins sensitize nociceptors)
- Exact mechanism unclear
Contraindications / Considerations
- Contraindicated in liver failure or active hepatic disease
Examples
- Acetaminophen 325-1000 mg PO q4-6h prn (max dose: 4000 mg/day)
- Standard dose: 1000 mg PO TID
Non-Steroidal Anti-Inflammatory Drugs (NSAIDs)
Mechanism of Action
-
Non-selective inhibition of COX-1 and COX-2 enzymes
-
Blocks arachidonic acid conversation to prostaglandins which sensitize nociceptors and cause inflammation
-
Reduces pain transmission and activates descending inhibitory pathways in brainstem
-
Particularly effective for bony pain (eg. mets)
Contraindications / Considerations
Contraindications:
- Recent MI (except aspirin)
- Perioperative period of CABG
Relative contraindications/avoid:
- Bleeding disorders
- Prior to surgery or invasive procedure
- Peptic ulcer disease
- Renal disease
Examples
- Ibuprofen (first-line)
- Naproxen (first-line)
- Diclofenac (oral, parenteral, or topical)
- Indomethacin
- Meloxicam
- Aspirin
Selective COX-2 Inhibitor
Mechanism of Action
- Selective inhibition of COX-2 reducing prostaglandin production
- COX-1 sparing reduces gastrointestinal risks
Contraindications / Considerations
- Preferred second line for mild-to-moderate
- Alternative to NSAIDs in patients with peptic ulcer disease
Caution in use:
- Renal disease
- Cardiovascular disease
Examples
- Celecoxib
Sodium Channel Blocker
Mechanism of Action
- Binds to voltage-gated sodium channels in nociceptive neurons, stabilizing the membrane and preventing action potential propagation
- Roughly similar to Toradol in usefulness
Contraindications / Considerations
- Take first dose on empty stomach
- Strong CYP450 inhibitor
Avoid use in:
- Severe hepatic impairment
Examples
- Suzetrigine (available in US)
Opioids
Mechanism of Action
- Binds to mu, kappa, and delta receptors presynaptically to inhibit Ca channels and neurotransmitter release responsible for pain conduction
- Mu: analgesia, respiratory depression, miosis, GI motility issues
- Delta: analgesia, convulsant, antidepressant
- Kappa: ?analgesia, anticonvulsant, dissociative/dysphoria, sedation
Indications
For chronic non-cancer pain, a trial of opioids is indicated if:
- Nonopioid pharmacotherapy and nonpharmacological therapy has been optimized
- Patient does not have current or past substance use disorder, psychiatric disorders, past history of opioid overdose, and other therapy has been optimized
A trial of opioids may be considered in patients with history of substance use disorder but shared decision-making should be used.
In patients with a history of mental illness or active mental health disorder, a trial of opioids is not recommended.
Contraindications / Considerations
Monitoring:
- Monitor for respiratory depression in first 72 hours after initiating or after increase of dose
- Oxycodone: not recommended for perioperative/postoperative in opioid-naive patients
- Tramadol: not recommended with epilepsy
Side effects to treat:
- Sedation (usually an accepted trade-off)
- Nausea (ondansetron effective)
- Constipation (bowel protocol, eg. PEG3350)
Contraindications:
- Asthma
- Bowel obstruction
- Biliary colic
- Head injury
Examples
By strength
Weak opioids (partial agonist activity to mu, and ceiling dose):
- Codeine
- Tramadol
- Tylenol 1, 2, 3 (compounded codeine with Tylenol)
- Percocet (oxycodone 5mg + Tylenol)
Strong opioids (no ceiling effect, titrate until analgesia achieved or side effect dominant):
- Morphine
- Hydromorphone
- Oxycodone
- Fentanyl
- Methadone
By release
- Immediate-release
- Sustained-release
- CADD or PCA pump
Prescribing Practices
Out-Patient
Dosing
- Daily dose should ideally be ≤80 mg morphine equivalents daily
- Daily dose should seldom if ever exceed 150 mg morphine equivalents daily
- The lowest effective dose should be used
Intervals
- Tapering should be offered to the patient every 6-12 months once main management is stable
Opioid contract
- A contract can be used as an educational tool (not required by CPSO nor recommended by guideline)
- Outlines expectations for prescribing opioids; components include:
- Only obtaining prescription from one physician
- Purpose of the opioids and the expectations of its benefits
- Taking medication as prescribed including dosing and frequency
- Understanding risks (eg. driving risk, complications, side effects)
- Safe storage
Urine toxicology screen
- Can be used to identify opioid misuse
In-Patient
Dosing
Immediate-release:
- Dose q4h regular
- Breakthrough dose of 10% of total daily regular dose q1h prn pain
Sustained-release:
- Dose q12h or q8h
- Breakthrough as above
CADD or PCA pump:
- Continuous infusion - basal dose (mg/hr) + bolus dose (mg)
Fentanyl patch:
- Q72h, ~12 hrs to start/stop
Adjustment/titration
Opioid doses are adjusted after steady state (5 half-lives)
- For immediate release, titrate daily
- For sustained release, titrate q3 days
If switching from IV to PO, increase by 2x to account for bioavailability/absorption.
Titration:
- If ≥3 breakthrough doses in 24 hours (exception: if there was a need such as PT appointment)
- Options:
- Increase by adding breakthrough to regular to make new regular, then generate a new breakthrough dose using 10% rule
- Increase 25-50% for mild-moderate pain, 50-100% for severe-uncontrolled
- Remember to check for causes of increasing pain
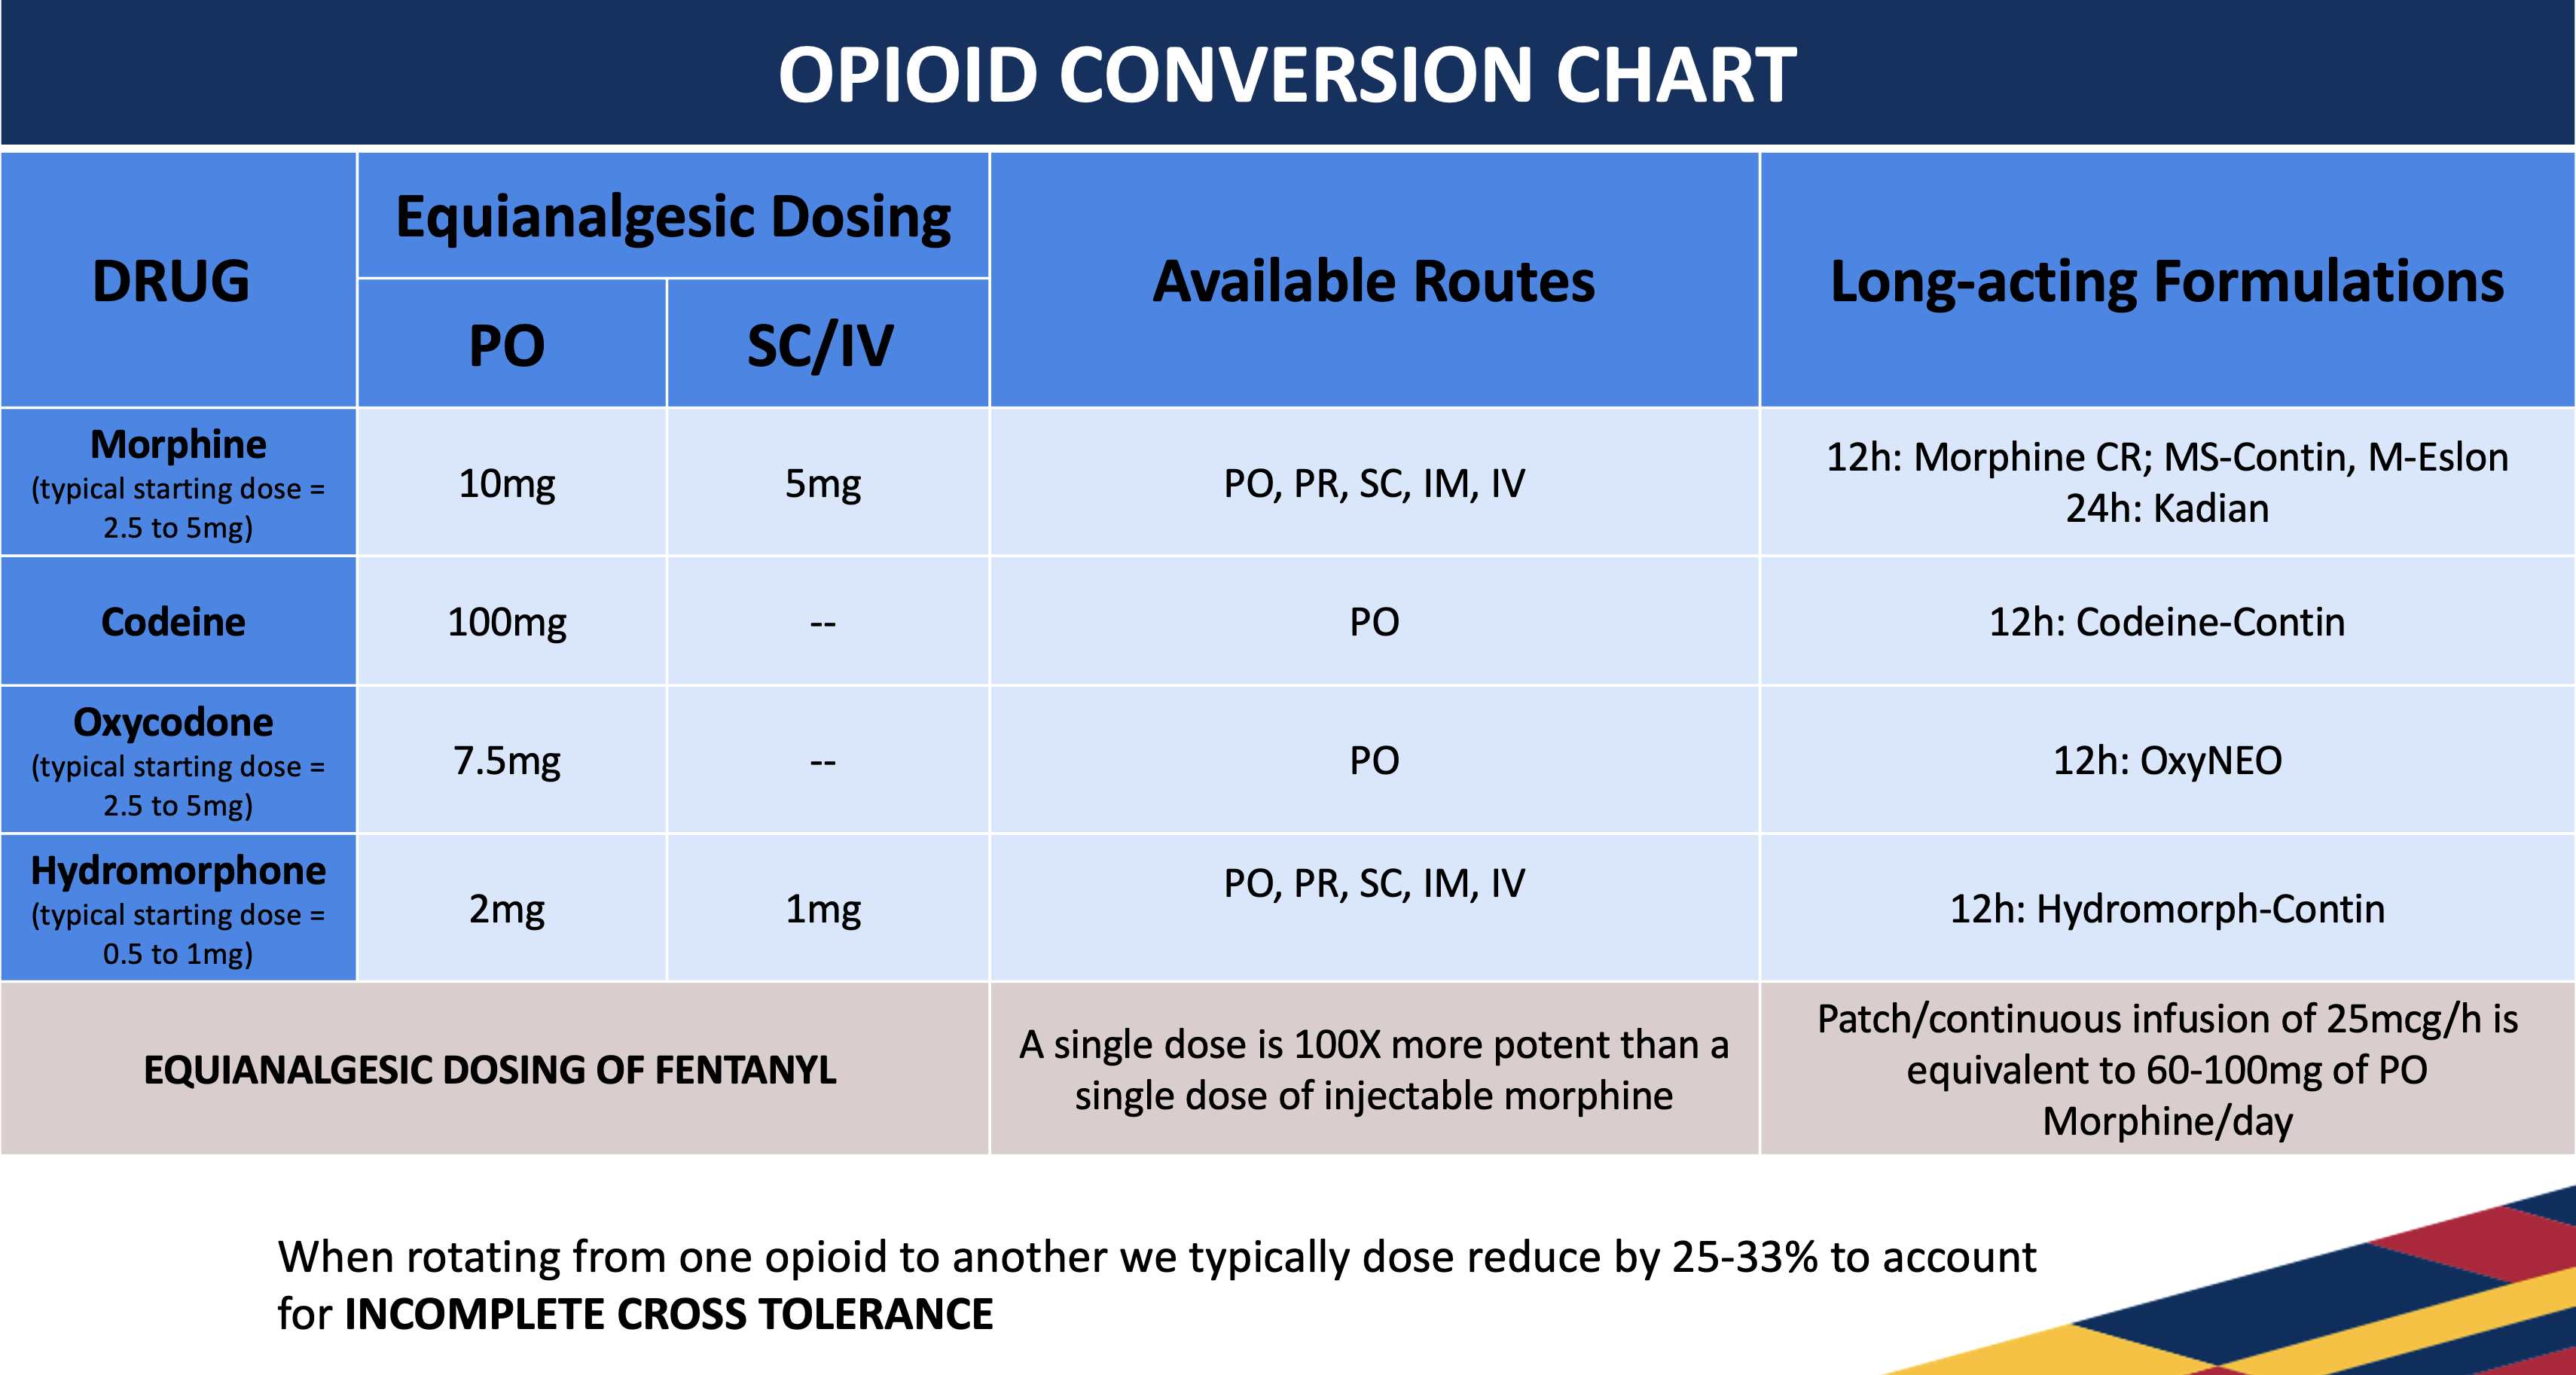
Opioid Conversion Chart
Adjuvant
Anticonvulsants
Mechanism of Action
- Stabilizes neuronal membranes by blocking voltage-gated sodium or calcium channels, suppressing ectopic firing and hyperexcitability
- Gabapentinoids bind to a2g subunits which inhibit calcium influx and excitatory transmitter release
Contraindications / Considerations
Limited evidence in use:
- From postherpetic neuropathy and diabetic peripheral neuropathy
- Short durations and lack of head to head comparisons
Examples
- Gabapentin
- Pregabalin
- Carbamazepine
Muscle Relaxants
Mechanism of Action
- Inhibits neurotransmitter release and postsynaptic activity in the spinal cord to reduce muscle tone and spasm-related pain
Contraindications / Considerations
Examples
- Cyclobenzaprine
- Metehocarbamol
- Baclofen
Antidepressants
Mechanism of Action
- Inhibits serotonin or norepinephrine which boost descending inhibitory pathways
- Activates a2-adrenergic receptors to suppress ascending pain signals
- Has additive benefit of treating psychological elements of pain
Contraindications / Considerations
Examples
Tricyclic antidepressants
- Amitriptyline
- Doxepin
- Clomipramine
SNRIs
- Duloxetine
- Venlafaxine