creation date: 2026-05-04 18:47
tags: Pathologies
Acute Otitis Media
Background
Definitions
Acute otitis media (AOM) is a common infection in children, and is most prevalent in children aged 6-24 months.
Acute otitis media: acute bacterial infection of the middle ear fluid
Otitis media with effusion: middle ear fluid that is not infected; also known as serous, secretory, or nonsuppurative otitis media
Middle ear effusion: fluid in the middle ear cavity, occuring in both AOM and OME
OME and AOM are part of a spectrum with OME frequently preceding AOM.
Etiology
Bacterial pathogens
- Streptococcus pneumoniae (15-25%)
- Haemophilus influenzae (35-60%)
- Moraxella catarrhalis (15%)
- Group A Streptococcus (2-10%)
- Staphylococcus aureus (uncommon)
Viral pathogens
- RSV
- Rhinovirus
- Influenza virus
- Parainfluenza virus
- Adenoviruses
- Human metapneumovirus
- Coronaviruses
Multibacterial and co-infection of bacterial and viral infections are common in patients with recurrent AOM.
Pathogenesis
The middle ear is a narrow chamber that is part of a system including the nares, the Eustachian tube, and the mastoid air cells. Pathogenesis of an at-risk child generally involves the following sequence:
- Patient is colonized with an otopathogen
- Antecedent event such as upper respiratory tract infection causes inflammatory edema of the respiratory mucosa of the nose, nasopharynx, and Eustachian tube
- Inflammatory edema obstructs Eustachian tube isthmus (narrowest part)
- Obstruction causes poor ventilation and negative middle ear pressure; secretions produced by middle ear mucosa accumulates
- Viruses and bacteria in upper respiratory tract enter middle ear via aspiration, reflux, or insufflation
- Microbial growth in secretions results in suppuration with clinical signs
- Effusion may persist for weeks to months following sterilization of middle ear
Clinical Presentation
Signs & Symptoms
Symptoms include:
- Ear pain
- Ear rubbing
- Hearing loss
- Ear drainage
- Fever (although temps >40 should raise suspicion for bacteremia or another source)
Manifestations may be nonspecific in infants or young children.
Complications may be present which includes:
- Postauricular swelling and protrusion of the auricle (mastoiditis)
- Vestibular symptoms with or without tinnitus or nystagmus (labyrinthitis, mastoiditis, cholesteatoma)
- Cranial nerve palsies
- Meningeal signs, cranial nerve deficits, focal neurologic findings
Otoscopic findings include:
- Fluid-filled middle ear
- Bulging, opaque, yellow, or white tympanic membrane
- Decreased or absent mobility with pneumatic otoscopy
- Perforation of tympanic membrane with acute purulent otorrhea (note, otitis externa needs to be ruled out)
History & Physical Exam
Accurate assessment is important to avoid unnecessary antibiotic use. History includes:
- Recent symptomatic URTI (risk factor for AOM for age <1 year)
- Past history of AOM
Physical includes otoscopy and assessment for complications.
Risk Factors
Risk factors include:
- Age (most important)
- Family history
- Day care
- Tobacco smoke and air pollution
- Pacifier use
- Supine feeding
Diagnosis
Criteria
Diagnosis of acute otitis media is made clinically. It is important to distinguish AOM from OME to avoid antibiotics overuse.
Diagnosis can be made in children with middle ear effusion and acute signs of middle ear inflammation. Generally, this is either:
- Bulging of the tympanic membrane (most specific sign of inflammation)
- Perforation of TM with acute purulent otorrhea if acute otitis externa has been excluded
Work-up
Additional workup is generally not necessary as diagnosis is readily made and treatment empiric.
In cases of toxic appearing patient, is immunocompromised, or was refractory to previous antibiotic therapy, etiologic diagnosis may be made through tympanocentesis for culture.
Differential
The main consideration is otitis media with effusion. This is distinct there are no signs of inflammation.
Other conditions corresponding to nonspecific findings include:
- Red tympanic membrane - vascular engorgement due to crying, high fever, URI
- Decreased mobility of TM - myringosclerosis
- Ear pain - otitis externa, ear trauma, throat infections, foreign body, TMJ syndrome
Red Flags / Complications
Untreated acute otitis media may result in:
- Hearing loss (conductive, due to effusion)
- Perforation of tympanic membrane (increased pressure causing ischemia and necrosis)
- Myringosclerosis
- Retraction or collapse
Unresolved or complicated AOM may become chronic (chronic suppurative otitis media). Other sequelae conditions include:
- Mastoiditis
- Cholesteatoma
- Spreading of infection to other parts of the ear and CNS.
Management
Pain Management
As ear pain is a common chief complaint, whether antibiotic therapy is administered or not, pain management should be provided.
This consist of ibuprofen or acetaminophen. In refractory cases, topical procaine, lidocaine, or cinchocaine are reasonable if the TM is intact.
Therapeutic tympanocentesis are rarely done but may be an option (refer to ENT).
Antibiotic Therapy
Prior to initiating antibiotic therapy, confirmation of diagnosis should be made. Specifically, the TM should be visualized and diagnostic criteria met.
The use of empirical antibiotics depends on the necessity (vs. spontaneous resolution) and side effects.
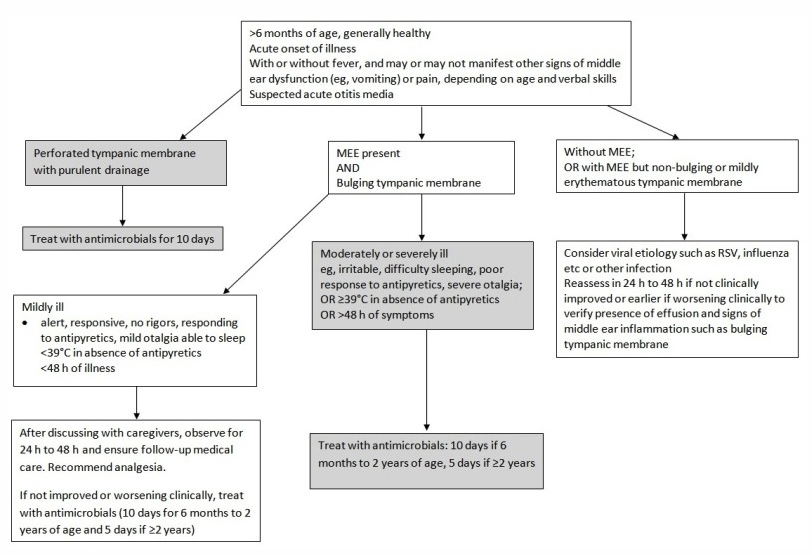
For mild disease without complicated features, a watchful waiting period of 24-48h is acceptable followed by reassessment or instructions for expectant antibiotic prescription.
For moderate to severe disease, or disease with complications, immediate antibiotics are warranted.
For disease with mild or without middle ear effusion, viral etiology is likely and antibiotics are unnecessary unless clinical worsening.
This is summarized by the CPS flow diagram:
Antibiotic options
First line (no penicillin allergy):
- Amoxicillin (x 10 days for <2 years old or risk factors/complications; x 5 days for ≥2 years old)
- 75-90 mg/kg/day divided to BID capsule or suspension
- 45-60 mg/kg/day divided to TID capsule or suspension
First line (penicillin allergy with non life-threatening reaction):
- Cefuroxime-axetil 30 mg/kg/day divided to BID or TID tablet or suspension
- Ceftriaxone 50 mg/kg IM or IV daily x 3 days
Second line (no improvement after 2-3 days):
- Amoxicillin-clavulanate
- If ≤35 kg: 45-60 mg/kg/day divided to TID x 10 days (400mg/5mL 7:1 suspension) – note: keeps clavulanate dose <10 mg/kg/day (more associated with diarrhea risk)
- If >35 kg: 500 mg tab PO TID x 10 days
References
Tools / Guidelines
Additional Reading
CPS - Management of acute otitis media in children six months of age and older